Showing posts with label PCM. Show all posts
Today -- The worst ever ending??
5/08/2009 06:29:00 PM | Author: fadzly
Late

Today, as always, i woke up at 8.30a.m and class should be start at 8.00am. But then later, i was told that the class will start at 9.30am. So i sambung tido la.. another 15 minutes i woke up, prepare to iron clothes. I relax2 je.. Raffiq already went to the class. I thought i was on time, then i simply go la to the clinic. Rupenya, WTF we should be in clinic at 8.00a.m to clerk patient then present at class at 9.30am!! Dahla come 15 minutes lambat, i even didn't bring my pen and my note! ishk2...

Clerking & Presenting Case

When Dr Sajar ask me what do you see down there? I said i didn't know we should be there earlier.. damn... Good things got Syud, she saw many patient today and present alone with zawati.. LoLZ.... So i just add abit of discussion bla bla bla..

Ending

It started like this, after all the long discussion we have reach the end of it, and Dr Sajar asking, whether you have any question related to PCM? Then Syud asking related to basic or something like pathophysiology. It suppose to be a happy ending. I never thought that because of my act mumbling to Zawati (and i forgot y i mumble), Dr Sajar become angry.. I never realize it, until the end of the class, all blame me that Dr Sajar was suddely raised her voiced.

Quotes from my classmates

Dr Sajar tibe2 berubah muke, tinggi suara

Die bengang start when Syud tanya pasal physio yang tak penting pastu when tgk muke ko tgh mumbling die terasa giler dan terus cakap if you dont like how i'm teaching bla, bla, bla...

Aku da rasa lain dah bile die cakap yang die tak kisah sama ada kamu datang kelas die atau tak. Die tahu yang kite tak datang tiap2 hari pukul 2 tu.

In the end it's up to you whether you are really desire(?) to pass the exam

Why? why? why?

I never and ever in my mind talking bad things about her. Did i?
I've been always respect her as my teacher. Maybe on that time I and that day, i'm not....
After what i did today do i really respect her? after came late, didn't bring pen, notes, etc?

Sorry

Sorry for everythings I've done.. I didn't mean it.. Maybe it's time for me to change my attitude.. Thanks for making me realising it..

________________________________

Connector

But that was the bad part.. hehe, Now is the syok part..
Today we trying hard to get our internet back after college has cut down our wire to the router. After thinking and brainstorming, we are now using BUNBUN's idea where the net will be available only after working hour and also weekends!! So we set up a new temporary wire which we only put it during the time set. We've make our own wire which is long and cut it into two. But the problem is now, we don't have any connector.. A bit relief when Teck Siang gave us a connector, but.... it's broken. Sigh... Then again, i dont wanna drive to digital mall and only buy the RM5.00 connector. Thus I've an idea. How about we build our own connector! lolz. You might be surprise how we made our own connector. It comes from a switch/hub!! LOLZ


The connector tek siang bagi.. Hampeh


Ni la bahannyer!! D-Link Switch 5 port!


All the things above we trash it.. The only thing we use is....


The port!! yes!!


A bit of wiring.. Lolz.. Simba managed to plaster the copper wire..


Nice art rite for a final year (extended) medical student.. kahkahkah!!

Thanks to Simba, Ronin and also last but not least thanks but no thanks for your connector Tek Siang. We're so tired testing, try and error for almost 4 times changing the wire head when we thought that the wire had problems. The connector, we managed to do that 2 times before we really made it for real by using coppers in the hub instead of using wires which were easily lose to the connector..


Aaahh.... at last.. internet~~syoknyer...

So is this happy ending?? Of coz is happy! I can download my movie again tonite!!!
read more about“Today -- The worst ever ending??”
Topic: Osteoporosis
5/04/2009 05:30:00 PM | Author: fadzly


Why me so bother talking about osteoporosis? Because Dr Sajar told so.. muahahaha... Osteoporosis is under group of metabolic bone disorder.

Definition
Osteo - Bone; poro - Pores; osis - condition
Apleys: Can found any.. LoLZ
Stedman: reduction in quality of bone or atropy of skeletal tissue; occurs in postmenopausal women and elderly men, resulting in bone trabeculae that are scanty, thin, and without osteoclastic resorption

Risk factor

Why so important of knowing the risk factor? So we can screen early ler.. Later i will talk how do we screen. Of coz almost all women who are menopause will get this osteoporosis, but if patient got +ve risk factor, it might accelerate the osteoporosis so it's important for us so we can prevent it earlier

Risk Factors are (from apley):
  1. First Degree family history of Osteoporosis
  2. Ectomorphic somatotype???
  3. Hysterectomy done before
  4. Cigarette Smoking
  5. Dietary faddism?

WTF is ectomorphic somatotype?? Stupid apley. That's y i never like this book. The book is so simple without explanation.. Hate it so much.. nway.. just forget about it now..

If u are 70 years onwards, additional factors come into play.
  1. Diminished activities
  2. Chronic illness
  3. Dietary deficiency
Clinical features
Basically clinical features depend on which fracture site it occur.

Hip Fracture
Hip fractures are a major cause of loss of independence in older women and men. Overall about half of hip fractures are intertrochanteric and the others are femoral neck fractures. In older women the proportion of trochanteric fractures increases. Trochanteric fractures, but not femoral neck fractures, are related to bone density. Femoral neck fractures, on the other hand, may be more related to mechanical factors. The vast majority of hip fractures occur after a fall. About 5% appear to be "spontaneous" fractures, in which the patient feels a fracture and then falls.

Vertebral Fractures

About 60% of women with compression fractures
do not realize they have had a fracture! Vertebral compression fractures vary in degree from mild wedges to complete compression. The symptoms also vary, but the degree of compression is not necessarily related to the amount of pain. It is possible that some of the fractures occurred gradually and therefore did not cause acute pain. When women and men do suffer painful compression fractures, the pain usually lasts from 1 to 2 months, is localized to the back with accompanying muscle spasms, then gradually subsides macam simple muscle strain except lebih lama skit. Usually patients with continuing severe pain should be evaluated for other pathologic etiologies of the fracture, especially
malignancy or myeloma. Persistent pain can also be caused by continuing fracture, muscle spasms, spinal stenosis, or degenerative joint disease.

Wrist Fracture
Wrist fractures are more common in women who are 50 to 60 years old. These are caused by falls or other trauma. Osteoporosis does not appear to impair the healing of the wrist fractures, and they cause only short-term disability.

Others such as body shape and consequences
Kyphosis, Heigth loss, Protruding abdomen, decrease pulmonary capacity, reflux esophagitis


Investigations
Xrays

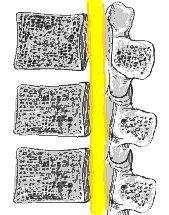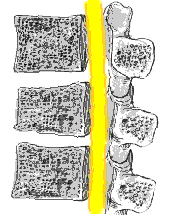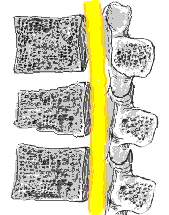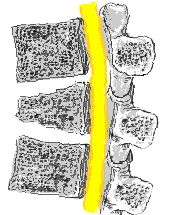
To correctly interpret a spine xray, it is important to know the definition of a vertebral fracture, which is not quite as straightforward as it first appears. A vertebra can be considered fractured if the
anterior height is 80% or less of the posterior height. A new fracture requires loss of at least 20% of anterior or posterior height. See picture on left.


Xray of the long bones also typically shows an osteoporotic fracture. Usually there is a general reduction in radiographic bone density and abnormal thinning of the cortices. Therefore, here comes DEXA in terms of measuring bone density more accurately

DEXA
For medical student, by knowing what full name of the DEXA is sufficient. No need to know it in detail. Using DEXA is a gold standard to diagnose osteoporosis. It came out in my EOP, 2 years ago, LOLZ. However some centres, DEXA scan were used alot in terms of screening to those with high risk. Now you see the reason why we should know the risk of having it! However it still controversial..haha..

Prevention
  1. Dexa scan for those women who have multiple risk factor particularly those with suspected low oestrogen or some other bone-losing disorder, and those who have suffered previous low energy fracture at the menopouse
  2. Calcium and Vitamin D supplement
  3. Avoid smoking and alcohol consumption
  4. Oestrogen medication (Hormone Replacement Therapy) is the most effective way of maintaining bone density. There was question related to PCM OSCE where we need to advice the patient of having HRT, but the problems about HRT are the complications.
  5. The newest drugs is Biphosphonates. It is a useful alternative to HRT. Biphosphonates have been shown to prevent bone loss and the to reduce the risk of vertebral and hip fractures.
Treatment
Managed the fracture first - Internal fixation, rehabilitaion.
Then genaral treatment - Vit D and Calcium supplement, diet with this elements, expose to sunlight, exersice and treatment with Biphosphonates or HRT should also be considered to prevent further loss.

A nice Clinical Practice Guideline you can download here
There is also some Orthopaedic book i like to share. Click here
read more about“Topic: Osteoporosis”
May 1st - holiday!! 2nd Question!!
5/01/2009 10:37:00 AM | Author: fadzly
Okay, because today is holiday, i'll continue happily typing the 2nd question for you all.. haha

Note: This question basically a short answer question, which might come out in the END OF POSTING test, OSCE, and also long case exam.

Mrs. Wee a 56 years old clerk has hypertension for the pass 1 year. She's currently comes for follow-up. She on tab amlodipine 10 mg daily. His blood pressure (BP) is 150/100 mmhg. Discuss the management of this patient. (10 marks)

So like always address the issues first! So what are the issues here?

Hypertension (HPT) for the pass 1 year. So we need to assess her IDEA about the HPT.

Her BP was 150/100. What do you think this is? Basically in any disease (i mean any medical or psychiatric illness) when the disease is not improving, there are 3 things to bear in mind.

1) COMPLIANCE
2) DOSAGE
3) WRONG DIAGNOSIS

So we need to assess all this three things first. In this case, usually the compliance and the dosage are all we talk about.

Then the other issues are to establish the degree of control of disease process

Then is there any complication from the disease?

And is there any co-morbid condition such as Diabetes, Obesity

Then after addressing the issues we tackle it one by one.. ok?

So answer should be like this

- I would like to assess this patient Idea about Hypertension. How much the patient knows about hypertension? How much the patient concern about the disease affect to his life, family, work?
- Then i would give top up the information and re-educate him so that the patient knows adequately about HPT, such as complication of the HPT. I would also like to tackle the biopsychosocial problems accordingly.
- I would like to assess this patient compliance. Did the patient compliance to medication? Did the patient compliance to the advice?
- If not why? Is there a problem? - Side effect? no access to medication such as patient poor, home is far, no transport, no clinic nearby? No one take care of him? Traditional medicine
- If compliance is the problem managed accordingly by giving education on medication, emphasis again about pharmacology and non pharmacology management, stop the traditional medicine.
- If the patient can’t tolerate the medication, such as side effect, change other type of drugs. If SE is not a problem, i would try to increase the dosage of the drug.
- Assess the patient compliance to advice and clinics. Did the patient go for follow up regularly? Did the patient have BP monitoring at home?
- I would like to emphasis on Non pharmacology management such as exercise regularly 30 minutes a day 3 times per week, eat healthy diet, less sugar, less fat diet, etc
- I would like to referred the patient to dietician
- I would like to assess any complication from HPT by doing CVS examination, EYE- ophthalmoscope and also do some investigation such as Urine dipstick, UrineFEME for protienuria, ECG for ECG changes.
- I would also want to assess this patient co morbidity such as DM or obesity by doing BMI, FBS, and cholesterol level.
- I would like to follow up the next 3 months or 4 months to monitor the progression.

I do agree with it's a bit wordy and difficult. Dr Sajar said, we just need a lot of training, that’s all. Good luck in your study! Till we meet at the next question! haha

read more about“May 1st - holiday!! 2nd Question!!”
Hari ke 11
4/30/2009 12:58:00 PM | Author: fadzly
Today Dr Sajar was to busy to have a class. Raffiq today gone with the wind.. He went to the GP earlier to get a medical check-up for his headache. He sent me a sms, he said his BP was high and his Cholesterol was also high. It might be the cause of the headache. But after that he's gone nowhere. I think he went back to JB, and later goes to Kelantan to meet his ehem ehem..

Today job was to be with Dr Nawar's wife..Dr Wan Noor Azlin.. hehe.. She was so friendly to us, and we manage to present some case to her. I presented DM case today. I managed to do peripheral neuropathy examination, ophthalomoscope examination and do RBS. Zawati presented some unknown diagnosis.. haha.. oldfolks always like this. They always anxious that something serious might happen to their body. Today cases are mostly pain on musculoskeletal, and some of them, Dr Noor managed to get an Xray done, and some of them also referred to Orthopaedic..

We went back at 12pm, then i met our old friends Adlisan coming from Kelantan using Air Asia. hehe, i'm smiling. Mangsa sudah datang.... Apa lagi, ask him to blanja me makan Pak Ali la.. hahahaha... I ask him makan pak li, later after eating, i buat2 forgot that i didn't bring my wallet.. muahahahah... So why did he come anyway?? Syafiq is getting married this Saturday. That's y he come, in order to ask syafiq to do the same for him the next week! Gothca!
read more about“Hari ke 11”
The 10th day of my 6 months
4/29/2009 05:47:00 PM | Author: fadzly
Woke up early?

So? What i do today? Got up early in the morning. i mean not early, 9.10 am.. In my timetable given by department, class start at 9.30. I'm not in a rush anyway, because hospital was just nearby my college. Then later when i came, Dr Sajar was there. She claims that she was there waiting us at 8.00.. owh.. so pity.. we all except Syud was coming at 9.30am. Then the dept get one of our phone number so that in case of something happen, they will call us.. Sorry Dr Sajar, she was so busy this week because of the ongoing Master's Exam now. That's why a lot of unknown people in the college currently.

Class

This time she managed to get us a past year questions.. It seems to be simple, but i thought it was challenging. There is 3 scenario question, basically all of them can be in the paper, OSCE or long case. Ok i managed to get the question in my note, roughly let see the question!


Question One

Mrs Tan 38 years old teacher present to the clinic with a 6 months history of lower abdominal pain, bloated, increased flatulance and diarrhoea. She stated that she can pass up to three loose bowel movement per day. There is no fever loss of wt(LOW) and loss of appetite(LOA). She was recently diagnose to have diabetes melitus and is on regular follow up and treatment.

1) What futher hx would you elicit and give reason? (8 marks)
2) Give 3 differential diagnoses (3 marks)

On physical examination, she looks well, in pink, not febrile and not in pain. Her height is 163 cm, and her weight is 67 kg. Abdomen was soft and there was very mild generalized tenderness.

3) What other physical examination and investigation would you like to do? (7 marks)
4) She has went to 4 different GP for the past 6 months and on antacids and antibiotics for her current condition. She request for a scope to be done. How do you respond to her request? (4 marks)
5) Outline the management for this patient (8 marks)


Discussion

This is a typical question in paper 1 for PCM every year. It just so typical that the question will start by asking, what futher hx u would elicit and what are the differentials?

So how to answer?

Read the questions first! Patient having chronic diarrhoea for the past 6 months. What do u think in your mind? Although the first question is what futher hx you want to take, but i usually start the 2nd question. So it will be easier for me to answer the 1st question, isn't it?

The DDx in mind are:
Irritable Bowel Syndrome (IBS)
SE of drugs such antibiotics, antacids, acarbose
DM
Hyperthyroidism
Diverticulosis

So the next things is to elicit history from the DDx above, rite?
Just answer like Steps on History Taking so you wouldn't miss a thing.

History presenting Illness
1) Characteristic of the stools, is it watery, mucous, blood, malaena, soft stool?
2) Any aggravating/relieving factor such as food stressor?
3) Any associated symptom such as nausea or vomiting
4) Patient malnurish? Assess the symptom of hydration status such as cramps, very weak or lethargy, thirsty, reduce urine output.
5) Symptom of thyrotoxicosis such as heat intolerance, increase appetite, reduce weight, eye problems

Then go to past medical and past surgical hx.
DM, HPT? any thyroid surgery - past hyperthyroidism

Drugs Hx
DM- what type of drugs? acarbose, metformin can cause diarrhoea
Antibiotics? Antacids? - can cause diarrhoea also

Dietary Hx?

Family Hx - any GI malignancy in the the first degree relatives?

Social Hx - any stress event occur? such as financial prob, increase workload as a teacher? - stress can induce diarrhoea

So basically, it complete. eventhough u might miss something, but hey, the above answers already make u have 8 out of 8.

Ok 3rd question.

The question already done Abdominal, take her BMI(overweight skit). What other PE?
Hehe.. simple la.. Same principle. Start with vital sign. Temperature, BP, pulse. Then do the Hydration status such as reduce capillary refils, skin turger, sunken eye etc..
Thyroid examination jgn lupa aaa..- Goiter, thyroid eye disease, pulse - AF, thyroid acropathy, proximal myopathy and etc.
Per rectal examination!!
and because patient has DM - check the eyes, peripheral neuropathy
Investigation such as - stools for culture, ova and cyst!!
then DM - we do, urine dipstick, UFEME, renal profile etc.
Haha.. 7 marks already~!

4th question.

4 marks means 4 point to be inserted... This question basically testing your generals knowledge. Even a layman can answer it.. If you meet this type of question, it means, it is a PCM question.

TIPS: PCM will always ask about this and the answer will always rejecting the patient request! The answer should be basically like this:

Firstly i would like to like to assess the patient consern about why she want to do scope? What does the patient thinks? Did she thinks about GI malignancy?
I would tell her that currently patient is not indicated for scope yet.(be in mind what are the indications for endoscopy)
Tell her about the complication if she done the scope such as bleeding, perforation etc, and it is costly wasting your money
But, if after stopping the antibiotic and antacid, patient still having diarrhoea then we can discuss about doing the scope later

Nice isn't it? If you have another type of answer pls do not hesitate to give it at the comment section.
Last.. Outline the management.

Outline management means make it simple. First of all address the issues that the patient having now.
Issues are Diarrhoea, DM, Overweight, Stress, Multiple GP, anxious about malignancy

Diarrhoea can be settle by non pharmaco and pharmaco. Non pharmaco such as stop triggering factors and takes care of her diet and takes plenty of water. Anti-diarrhoea can be given to her.
DM - Compliance to medication, healthy lifestyle, reduce intake of sugar, fats, eat a lot of fibres, reffered her to dietician.
Overweight - Lose weight, excersize regularly 30 minutes and 3 times a week.
Stress - Reduce stress by plan management, sleep adequately.
Reassure again that this is not due to malignancy and give simple explanation about symptom of GI malignancies.

That its.. Penat menaip.. 2nd and 3rd questions will coming.. later.. i nak eat first...

read more about“The 10th day of my 6 months”
Starting my diary with Vertigo?
4/29/2009 12:52:00 AM | Author: fadzly

Yesterday was the beginning of my 2nd week posting of my Primary Care Medicine and i've clerk one patient with a c/0 of dizziness. Ususally, i'll be given an hour to clerk. because i got this patient late, i have such a short time to clerk this patient. Patient is 38 malay lady works as a kindergarden teacher. She complaint of having dizziness for the past two weeks that are worsoning. However the dizziness have been there for the past 5 years already. But this time it was the worst and not relief by medication. At first i was thinking of Benign positional proxysmal vertigo (BPPV).

As a typical noob medical student, when we have a target, we cant think of other disease. I do manage to think other disease such as anaemia causing vertigo.

Time up! owh damn. i havent finish clerking and i didn't manage to do any of physical examination. my lecturer ask me to present the case. So as usual, i present in the way that i usually present. (haha). Dr ask me what the diagnosis. So i tell her the BPP

V and also the anaemia. As always, a typical lecturer will do is to ask alot questions regarding the history. haha.. i terkena so badly today.


History

Did you ask about anaemia? Did u ask about other things apart from lethargy, SOB etc? Owh damn... i forgot and blank.. then i ask what dr? lolz.... we shouldn't ask like that! kene lagi!

You need to ask about menstrual hx. Do u ask that? Do u ask about any cause of anaemia? Do u ask anything about bruises, jaundice, diet hx, etc2.. owh then i got it.. it's just the cause of anaemia.. Lolz. Of course i knew it, but then again, i cant relate it with the hx i take.. how pathetic..

Then the dr ask the patient to come in. This time dr take the 'proper hx'. The patient claim that she's having it since the day she delivered her last child. It was also associated with tremor, palpitation. and she said it again and again. She claim the dizziness also come during when she needs to see the principle, or need to get infront giving speech to the students. So what do u think the diagnosis now? Hehe.. wait till the end of the post..

So we do the maneuver to detect nystagmus to rull out BPPV, we do CVS also. But we didnt do any CNS examination. At the beginning, i was shock, but deeply in my heart saying thank god that the lecturer didn't ask me to do the worst examination ever - CRANIAL NERVE EXAMINATION.. haha.. Anyway we make it simple, dr have the diagnosis already. The lect says 'u all should think of Psychosocial also u know'. Immediately i think, what on earth vertigo related to psychosocial. So i took my oxford handbook and got to my vertigo page. (7th edition page 454). Now i know that vertigo can be true and false! aiyooo.. Oxford says, what is not vertigo is faintness may be describe as dizziness but often due to anxiety with associated palpitation, tremor and sweating. lolz.. i've study for 2 years and i still didn't know that vertigo(i meant dizziness) can be due to anxiety!! HAHAHA.. That's might be the case that i need to study extra 6 months..


Diagnosis

Just forget about it, it's happening already. So the diagnosis was Panic Disorder and we managed her by doing FBC, thyroid function test, and gave her anxiolytics which is benzodiazepine. Because my lecturer was so afraid of giving this drug due to the SE (addicted) she only dare to give her the drug for 3 days, lolz... Nevermind then, a psychiatric will give her more.. muahaha..


Conclusion

So in summary, dont think that vertigo is just due to the inner ear problems only. think generally such as anaemia, heart disease, thyroid and put the tumour at the last last last last part of differentials or the best is dont ever say it and try think of psychiatric.. hehehehe..

Just want to share some readings materials in the web about anxiety. Nice to read, really. The site shows ways to tackle your anxiety. http://www.treatment-for-anxiety.org/

Till we meet next time, nite..


Fadzly

read more about“Starting my diary with Vertigo?”